 How Oral and Injectable Glp-1s Work Differently
Imagine two travelers delivering the same message to your pancreas: one knocks gently at the gut gate, the other arrives by steady injection. Oral therapy must survive digestion, use absorption enhancers, and is prescribed as an Rx that acts through gut receptors and hepatic signaling. Injectable GLP‑1s bypass digestion, provide sustained bloodstream levels, and directly stimulate insulin and satiety centers.
Practical differences matter: oral molecules rely on timing with meals, titration, and sometimes face prior auth hurdles, while injectables often need fridge storage and a cold chain during distribution. Patients weigh convenience, needle anxiety, cost, and tolerability; clinicians balance titration strategies, side effect profiles, and real-world adherence when choosing the best individualized therapy monitoring closely.
| Route | Primary practical difference |
|---|---|
| Oral | Must survive digestion; meal timing important |
| Injectable | Stable bloodstream exposure; cold storage needs |
Comparing Blood Sugar Control and Weight Loss
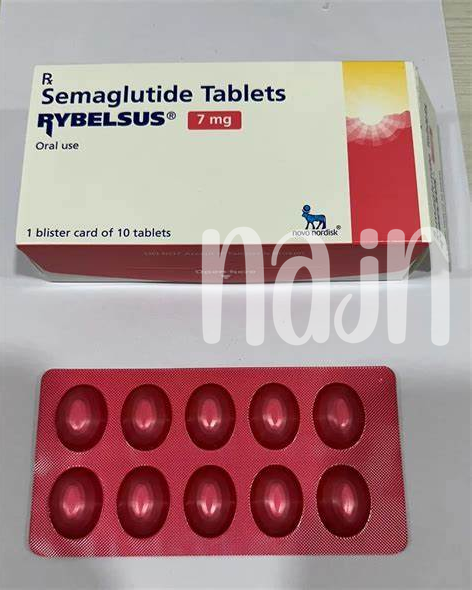
Patients describe switching to an injectable as a point: glucose numbers drop more steeply with weekly semaglutide injections, and weight loss tends to be larger and faster than with oral option. rybelsus lowers A1c reliably and supports modest weight loss when combined with lifestyle change.
In practice choice balances potency with convenience. Some patients prefer a pill to avoid shots and Rx logistics, while others accept injections for stronger results. Insurance hurdles like Prior Auth (PA) and formulary placement influence access, so clinicians weigh barriers as carefully as study data.
Dosing, Administration, and Convenience: Pill Versus Shot
Taking a pill like rybelsus feels instinctive: a daily tablet swallowed fasting with a sip of water and a wait before breakfast, while a weekly injectable demands learning injection technique and timing. Patients often trade the ritual of a morning pill for the predictability of once-weekly dosing.
Administration affects access: pills arrive as a straightforward Rx without injection supplies, but oral semaglutide requires strict timing to work. Injectables may need needle disposal and sometimes refrigeration, yet their levels simplify titration. Insurance hurdles through PBM can shape the route patients receive and affect real-world uptake.
For busy lives the choice is personal: those avoiding needles prize the pill's ritual, while people who prefer fewer pills welcome weekly shots. Travel, storage (some injectables are Fridge Drugs) and comfort with self-injection determine adherence, so clinicians should tailor plans to each patient's realistic goals.
Side Effects, Safety Signals, and Long-term Risks
Stories from clinic floors often start with nausea and early appetite changes—common with both oral and injectable GLP‑1s, though pills like rybelsus can irritate the stomach lining more than injectable formulations. Patients also report injection‑site irritation and transient dizziness; rare but serious concerns such as pancreatitis or gallbladder disease trigger urgent evaluation. Animal data showed thyroid C‑cell tumors for some molecules, so clinicians screen carefully and counsel about warning signs.
Longitudinal follow‑up emphasizes monitoring kidney function, mood shifts, and nutritional status, especially when therapies are added to a crowded Rx regimen. Coverage hurdles like Prior Auth (PA) approvals shape who gets treated and how promptly, affecting safety oversight and dose titration. Shared decision‑making and clear instructions promote adherence; patients should promptly report persistent abdominal pain, unexplained weight loss, or jaundice. Clinicians balance benefits with surveillance through periodic labs and counseling.
Cost, Insurance Coverage, and Real-world Access
Insurance hurdles can feel personal: a patient choosing rybelsus waits as clinical notes accumulate and a Prior Auth (PA) looms. Pharmacy benefit managers and rigid formulary tiers turn hopeful starts into phone calls, appeals, and sticker shock. Even when clinically appropriate, approvals can take days, creating gaps in care. Some clinicians mail sample tablets while others navigate step therapy, turning simple decisions into administrative marathons.
Practical choices hinge on price and convenience: co-pays, manufacturer coupons, and clinic sample programs can bridge the gap but often expire. Community pharmacies face "Fill Day" surges and patients may switch plans if access is inconsistent. Below is a quick snapshot:
| Barrier | Fix |
|---|---|
| High copay | Manufacturer coupon |
| PA delays | Pre-authorize note |
Who Benefits Most: Choosing the Right Patient
Patients with elevated A1c who prefer to avoid needles often favor an oral GLP‑1. A daily tablet fits busy lives, reduces pill burden, and feels less invasive than injections.
Those needing larger, sustained weight loss or robust glucose lowering may do better with injectables, which generally give greater efficacy and cardiometabolic benefit. Injectable therapy can be titrated more aggressively.
Cost, access and formulary rules matter: many insurers require Prior Auth (PA) or favor certain brands through PBM decisions. Clinicians should discuss out‑of‑pocket costs and coverage hurdles prior to prescribing.
Comorbidities — renal disease, gastroparesis, or GI sensitivity — plus adherence patterns guide choice. Shared decision making, realistic goals and regular follow‑up ensure the selected option fits the patient's life.
About Us
~

Hablo español. ¿Y tú?
Contact us
or
Use Google Translate
translate.google.com.
Visit us...


