 How Ozempic Actually Changes Appetite and Metabolism
Clinicians explain GLP-1 drugs act on brain hunger circuits, slowing gastric emptying and boosting satiety through hormonal signaling. Many patients liken the effect to receiving an Rx that resets cravings and reduces portion sizes.
Metabolic improvements follow: lowered insulin demand, modest resting metabolic changes, and shifting substrate use favoring fat oxidation. Titration and monitoring guide dose changes to preserve safety and minimize side effects.
Real-world outcomes require lifestyle support, regular Meds Check, and attention to storage like Cold Chain for injectable products.
| Effect | Result |
|---|---|
| Appetite | Reduced |
| Metabolism | Shifted |
| Dose | Adjustment |
Separating Weight Loss Effects from Diabetes Glycemic Control

In clinic I meet people hoping for quick appetite fixes; one patient described eating half portions after starting ozempic, which sparked real curiosity.
Scientific trials separate glycemic control from weight pathways, showing appetite centers and metabolism change independently during early titration and dose adjustments.
Clinicians emphasize that an Rx accompanies monitoring: blood glucose, lipids, and heart rate guide therapy beyond mere scale numbers and kidney function checks regularly.
Framing expectations reduces misuse; patients learn behavioral strategies, side effect recognition, and realistic timelines instead of chasing celebrity trends or quick fixes.
Safety Profile and Short Term Benefits Versus Unknowns
Patients often report rapid appetite reduction and early weight loss on ozempic, improvements that can feel dramatic in weeks. Clinical trials show meaningful glycemic and cardiometabolic gains alongside side effects such as nausea, constipation and injection-site reactions; most are transient and manageable with dose titration. Clinicians stress starting an Rx with clear instructions and follow-up to adjust dose and monitor labs, because short-term gains don't erase longer-term unknowns.
Longer-term safety—effects on pancreatic, gallbladder, and bone health, or on sustained weight set-point—remains under study. Real-world use sometimes treats ozempic as a quick fix, a 'Fridge Drugs' convenience for storage, increasing risk if monitoring lapses. Shared decision-making, regular Meds Check, and vigilance for rare but serious events help balance demonstrated benefits with uncertainty. Those with pancreatitis history, medullary thyroid cancer risk, or pregnancy need special caution and individualized counseling and monitoring together.
Misconceptions about Dependency and Appetite Suppression Risks
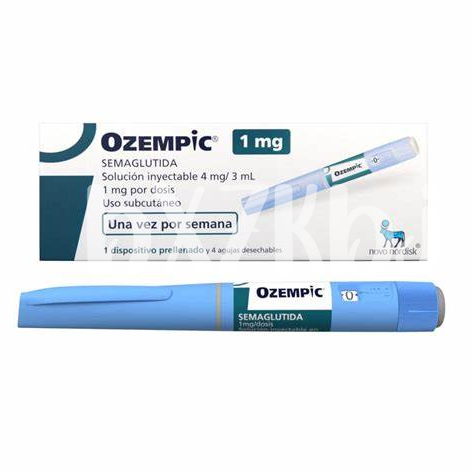
Patients often worry they’ll become dependent, imagining constant hunger control beyond treatment. Science shows neurohormonal resetting rather than addiction, not physical dependence.
Appetite suppression from ozempic is dose-dependent and often transient; careful titration and Rx monitoring minimize abrupt rebound and side effects for patients.
Clinically, semaglutide shifts satiety circuits without producing euphoria or craving typical of Narcs; this is physiologic adaptation, not substance dependence over time either.
Talk to a clinician about goals, dose changes, and duration; monitoring protects weight maintenance and addresses return of appetite when therapy stops safely.
Off Label Use, Celebrity Trends, and Ethical Concerns
High-profile endorsements and social buzz have turned ozempic into a cultural talking point, but the reality is more nuanced. Patients chasing quick fixes may seek an Rx - Prescription without understanding eligibility, risks, or long-term effects. Clinicians warn against following trends rather than evidence.
Ethical questions arise when supply strains affect patients who depend on therapy for diabetes. Insurance denials and PBM - Pharmacy Benefit Manager hurdles can compound inequity, while casual use at parties or by celebrities normalizes demand. Balanced policies and transparent prescribing prioritize patients' needs and trust.
Practical Guidance Who Should Consider Therapy and Monitoring
Begin with clear criteria: people with type 2 diabetes or obesity-related complications, a BMI over thresholds, and those who have tried lifestyle change with limited success often benefit. Discuss goals — glycemic control, weight reduction, cardiovascular risk— and set realistic expectations before starting an Rx medication.
Shared decision-making matters: discuss side effects, fertility or pregnancy concerns, and cost or insurance barriers including prior authorization. Coordinate with a multidisciplinary team so primary care, endocrinology, and nutrition counseling align.
Start low and slow; titration schedules and regular monitoring of blood glucose, weight, kidney function, and mood are essential. Plan follow-up visits, consider referral to a diabetes educator, and prepare exit strategies if benefits plateau or adverse events emerge.
About Us
~

Hablo español. ¿Y tú?
Contact us
or
Use Google Translate
translate.google.com.
Visit us...


