 Why Antiviral Treatment Matters in Pregnancy
Pregnancy alters immunity and priorities, turning routine infections into fraught decisions. When influenza strikes, rapid antiviral therapy can reduce illness duration and serious complications for the mother.
Treating fever and viral replication matters because high maternal fever early in pregnancy links to developmental risks, and severe maternal illness can prompt preterm birth. Antivirals are not mere comforts; they change trajectories.
Clinicians prescribe with context: evaluating timing, severity, and drug safety data before writing an Rx. Supply issues and logistics, like Cold Chain maintenance for some medications, also shape practical choices.
Framing treatment as risk mitigation helps patients make informed choices. Clear counseling, timely action, and follow-up transform a tense episode into managed care, balancing maternal health and fetal protection.
| Benefit | Consideration |
|---|---|
| Shorter illness | Prevents complications |
| Lower hospitalization | Cold Chain |
| Fetal protection | Minimal teratogenicity |
| Timely Rx | Counseling needed |
| Shared decision | Follow-up |
Understanding Safety Evidence for Mother and Fetus
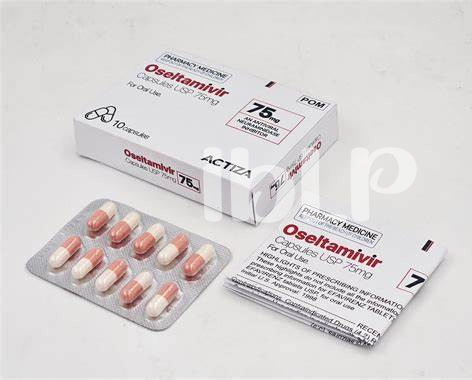
A pregnant patient describes fever and cough, prompting clinicians to weigh maternal health against fetal safety. Observational studies and randomized trials inform the risk picture for both mother and baby.
Overall evidence suggests oseltamivir reduces complications when given early, with no consistent signal for major birth defects. Most data come from cohort studies and vaccine-era surveillance.
Clinicians should discuss benefits, uncertainties, and likely side effects, document an Rx when indicated, and reassure patients about monitoring via registries and Cold Chain-aware supply for any needed generics and follow-up and close monitoring.
Balancing Maternal Benefits Against Potential Fetal Risks
A pregnant person with fever and cough often faces a wrenching choice: treating influenza promptly can prevent severe maternal complications and admission to hospital. Antiviral therapy, most commonly oseltamivir, reduces progression and is time-sensitive, so clinicians emphasize early evaluation.
Evidence from observational cohorts and registries shows no consistent increase in major birth defects after maternal oseltamivir exposure, though data are imperfect. Clinicians write an Rx and consider drug access, including generics and local formulary availability, while weighing gestational age and maternal comorbidities.
Conversations should frame absolute risks versus benefits, acknowledge uncertainty, and document informed consent. Prioritizing maternal respiratory stability often justifies treatment; close follow-up and neonatal surveillance ensure any rare outcome is identified and managed.
Clinical Guidelines and Timing of Antiviral Therapy
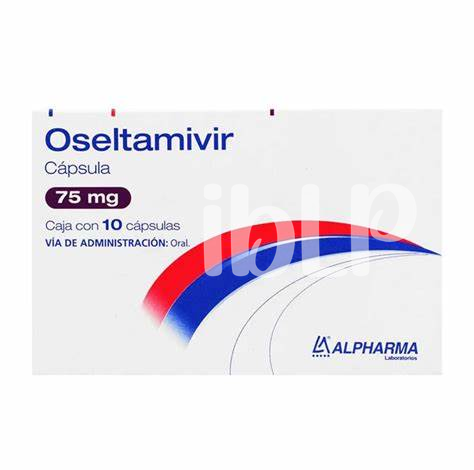
When a pregnant person develops influenza, clinicians urge prompt assessment; evidence favors early antiviral therapy, especially within 48 hours of symptom onset. Oseltamivir has the best safety data in pregnancy and is commonly recommended for severe illness.
Protocols balance maternal benefits against fetal concerns, and many hospitals provide an Rx - Prescription with clear Sig - Directions on a prescription for dosing and monitoring. In urgent cases treatment is started Stat - Immediately to reduce complications.
Follow-up checks response, adjusts therapy if needed, and records care fully in prenatal chart.
Common Side Effects and Rare Adverse Outcomes
Pregnant patients often worry about antiviral safety; clinicians weigh maternal benefit against fetal exposure. Early oseltamivir therapy reduces severe influenza risk, and clear Rx guidance helps streamline urgent care.
Commonly reported effects are mild gastrointestinal upset and headache; these usually resolve. Most hospitals use generics where appropriate, and counseling includes when to return for worsening symptoms or high fever.
Rare adverse outcomes are infrequent but discussed during consent; data support maternal benefit outweighing risk in severe cases. Shared decisions, clear Sig and follow-up improve safety and maternal confidence.
| Nausea | Common |
Shared Decision-making: Conversations, Consent, and Follow-up
In clinic, conversations often begin with a patient's fear of harming the baby versus the risk of untreated flu. Clinicians listen, explain evidence, and invite questions about treatment.
During counseling, clinicians make Quality Time to review benefits of antiviral therapy, alternatives, and the practicalities: timing, dosing, and whether an Rx will be needed and expected outcomes discussed.
Explicit consent includes describing common side effects, rare fetal outcomes, and the maternal benefits of early treatment; documentation and a clear plan for follow-up are laid out with timelines.
Patients are advised to report worsening symptoms Stat or side effects; planned check-ins, medication reconciliation, and coordination with obstetric care create continuity and empower informed choices and reduce anxiety.
About Us
~

Hablo español. ¿Y tú?
Contact us
or
Use Google Translate
translate.google.com.
Visit us...


