 Common Myths about Pregabalin and Where They Stem
Anecdotes ripple faster than data: stories of easy Script fills and shadowy Pharm Party exchanges seed fear. Myths often arise from isolated cases, tabloids, or confusing label language.
Once online forums amplify rare reactions, statistics get lost; a compelling testimonial beats bland percentages. Understanding study size, placebo effects, and real-world context flips fear into informed questions and clearer follow-up data.
Clinicians rely on trials and guidelines; separating myth from evidence helps patients ask better questions, request clear Sig directions, and pursue balanced, evidence-based care with informed consent and safe follow-up.
Safety Concerns Versus Evidence from Clinical Studies

When headlines alarm patients about lyrica, nuance disappears. Randomized trials and pooled analyses show pregabalin reduces neuropathic pain with a generally acceptable safety profile. These studies document predictable, dose-related effects and help separate uncommon harms from online anecdotes and sensationalized reporting and clinical practice.
Regulators require clear labeling and warnings based on trials, not anecdotes; clinicians weigh benefits against risks and individual comorbidity. Misinterpretations can arise when isolated case reports are amplified. Ask for a clear Script - Prescription plan, understand titration and titration-related dizziness risks, and prioritize evidence from randomized controlled trials over viral stories.
Patients should review renal function and concomitant meds with clinicians, who monitor somnolence and gait. Shared decision-making and a structured Meds Check reduce surprises. Discuss cost and availability, including Generics - Non-brand medications options, and insist on follow-up to adjust doses and minimize harms.
Addiction Risk Explained: Dependence Facts and Fiction
A friend once worried that taking lyrica would turn them into someone chasing pills; that fear often comes from stories, not data.
Physical dependence can develop with regular use, producing withdrawal if stopped abruptly, yet addiction involves craving and harmful behaviors.
Clinical trials show most patients using lyrica as directed do not become addicted. Clinicians write a Script - Prescription with clear Sig instructions and assess history; casual sharing at a Pharm Party increases harm.
Talk openly with your prescriber about prior substance use, start low and titrate, and plan gradual taper if stopping. This pragmatic approach acknowledges real dependence risk without stigmatizing effective relief provided by lyrica when used under supervision with careful follow-up.
Side Effects: Common, Rare, Manageable, and Misunderstood
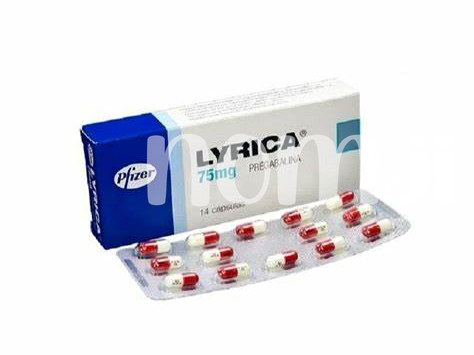
When people start lyrica they often trade dramatic stories: drowsiness, weight gain, or dizziness. Yet many reactions are mild, appear early, and settle with dose adjustment.
Common complaints like sleepiness or blurred vision come from nervous system dampening; clinicians usually manage these by changing the Rx or timing of doses. Rare effects—severe allergic reactions, vision loss, or swelling—are documented but uncommon.
Dependence worries make some avoid useful therapy, but withdrawal can be minimized by slow titration and supervised tapering. A pharmacist or Pharm Tech can be invaluable for counseling and spotting interactions.
Misunderstandings also arise when people mix meds, alcohol, or 'happy pills'; clear communication with prescribers reduces risk and helps normalize manageable side profiles. If symptoms persist, discuss alternatives and monitoring plans; labs or eye exams are sometimes recommended to detect rare but serious problems early and reviewed promptly.
Off-label Use Myths Versus Legitimate Therapeutic Roles
Patients often hear stories about lyrica used off-label for diverse problems; some arise from hearsay at a Pharm Party or a casual Rx, others from small studies. Distinguishing anecdotes from trials matters for safe, effective care.
| Condition | Evidence |
|---|---|
| Neuropathic pain | Supported |
Clinicians weigh trial data and patient goals before recommending off-label uses; some are reasonable alternatives when evidence is modest. Ask your prescriber about expected benefits, common harms, monitoring plans and alternatives. Shared decision making and careful titration reduce surprises and respect individualized risk and avoid unnecessary prescribing where possible.
Practical Guidance: Talking to Doctors and Tapering Safely
When you sit across from your clinician, tell a concise story: symptoms, previous treatments, goals and fears. Bring a list of current meds, doses and any reactions—this helps avoid dangerous interactions and supports shared decision-making. Ask about alternatives, expected benefits, and the usual Rx plan including monitoring.
When tapering, plan ahead with the prescriber: gradual titration reduces withdrawal and rebound pain. Never stop abruptly. Keep a written timeline, identify red flags, and arrange follow-ups or a medication review. If side effects emerge, report them early so doses can be adjusted or switched.
Document questions before appointments, ask for a hard copy of instructions, and clarify directions like timing and stepwise decreases. If follow-up is difficult, request telehealth checks or a pharmacist medication review for extra support. Safe tapering relies on planning, clear communication, and patience and realistic recovery goals ahead.
About Us
~

Hablo español. ¿Y tú?
Contact us
or
Use Google Translate
translate.google.com.
Visit us...


