 Why Ace Inhibitors Trigger That Annoying Cough
Many people describe an ACE inhibitor cough as a dry, tickling nuisance that appears weeks to months after starting treatment. The story is biochemistry made personal: ACE blockers raise levels of bradykinin and substance P in the lungs, increasing airway sensitivity and provoking a reflex cough. It’s not allergic, and stopping the Rx often stops the cough.
Clinicians look for timing, absence of fever, and cough quality before switching drugs.
| Mechanism | Effect |
|---|---|
| Bradykinin | Cough |
| Substance P | Increased sensitivity |
Who’s Most Likely to Develop Persistent Cough
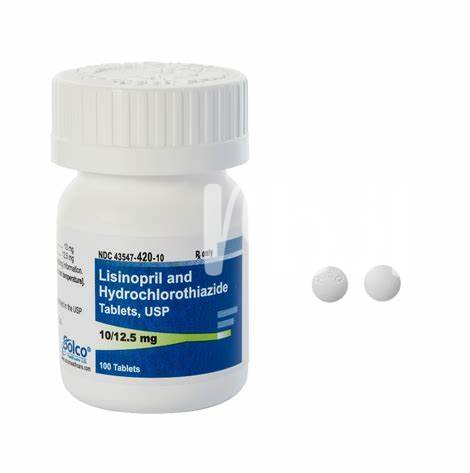
Imagine starting lisinopril and weeks later a dry tickle won’t quit — that’s common and predictable in certain people. Women and older adults report this cough more often, as do people with a prior history of asthma or upper airway sensitivity. Genetic and ethnic factors seem to matter, so some groups show higher susceptibility in studies.
Non-smokers appear paradoxically at greater risk, and multiple medications or a high pill burden can complicate the picture; always tell your clinician about all drugs and OTC treatments. The cough typically emerges within days to months and persists until the ACE inhibitor is stopped, so recognizing these risk patterns helps target a timely review of your Script choices and options.
Distinguishing Drug Cough from Other Respiratory Causes
When a persistent tickle follows starting lisinopril, the detective work matters. A drug-related cough often begins weeks after an Rx - Prescription is filled, is dry, nonproductive, and may worsen at night or with position changes. Unlike an infection, there is no fever, colored sputum, or clear response to antibiotics. Listening to timing, associated symptoms, and recent med changes points toward the cause. Patients sometimes confuse side effects with allergies, delaying helpful changes.
Clinicians will rule out asthma, GERD, postnasal drip, and viral illnesses by exam, chest imaging, spirometry, or trial of OTC - Over The Counter remedies. Stopping the ACE inhibitor under medical guidance or switching classes often clarifies diagnosis when cough resolves within days to weeks. Keep notes on onset, triggers, and other meds to speed a correct assessment and safer treatment plan and ask about safer alternatives.
When to Seek Medical Advice and Testing
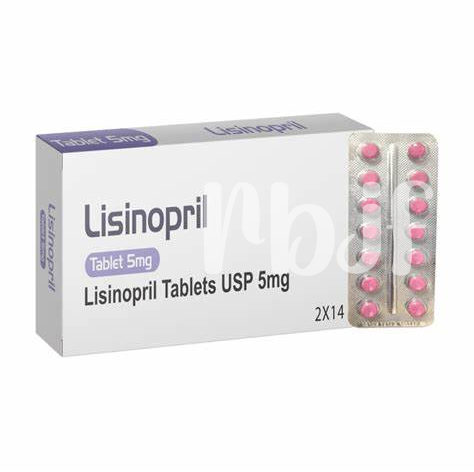
If a dry, persistent cough starts after beginning lisinopril, and it worsens or interrupts sleep, contact your clinician. Shortness of breath, wheeze, chest pain, fainting, or coughing blood are red flags needing immediate evaluation.
Your clinician will review your Rx list, other conditions, and timing of symptoms; they may order a chest X‑ray, spirometry, or basic labs. Sometimes a monitored trial stopping the drug clarifies whether the ACE inhibitor causes the cough.
Seek faster care if fever, weight loss, or swelling accompany symptoms. Pharmacists or Pharm Tech staff can suggest OTC measures for comfort, but avoid switching medications without medical guidance — alternatives exist and should be discussed before any change. Follow up if cough persists.
Safe Medication Alternatives to Discuss with Clinician
If lisinopril causes cough, discuss switching to an ARB (for example losartan) or a calcium channel blocker; both often relieve cough while controlling blood pressure. Diuretics like chlorthalidone may suit some patients. Mention allergy history and current medication list when talking with your clinician.
Ask about Generics availability, dose titration and whether a new Rx requires lab monitoring. Your clinician can balance efficacy, side effects and pill burden, and arrange follow-up. Never stop or change meds Stat without medical advice.
| Option | Class |
|---|---|
| Losartan | ARB |
| Amlodipine | CCB |
| Chlorthalidone | Diuretic |
| Generics | Available |
Practical Remedies and Lifestyle Tips to Manage
When a cough from lisinopril nags you, small comforts help. Start by avoiding irritants: smoke, strong fragrances and cold air, and keep humidity moderate. Steam inhalation or warm drinks can soothe the throat temporarily.
Saline nasal rinses and throat lozenges reduce postnasal drip and irritation; consider OTC antihistamines if allergies contribute. Stay hydrated and sleep elevated to limit nighttime coughing episodes.
Talk with your clinician before changing drugs—don’t stop a prescription abruptly. Ask about switching to Generics of other classes like ARBs if appropriate; sometimes dose adjustment or different timing eases symptoms.
Track cough patterns in a journal and mention them during medication review; persistent or blood-tinged coughs need Stat evaluation. Lifestyle changes bring relief.
About Us
~

Hablo español. ¿Y tú?
Contact us
or
Use Google Translate
translate.google.com.
Visit us...


